A command center for the shift
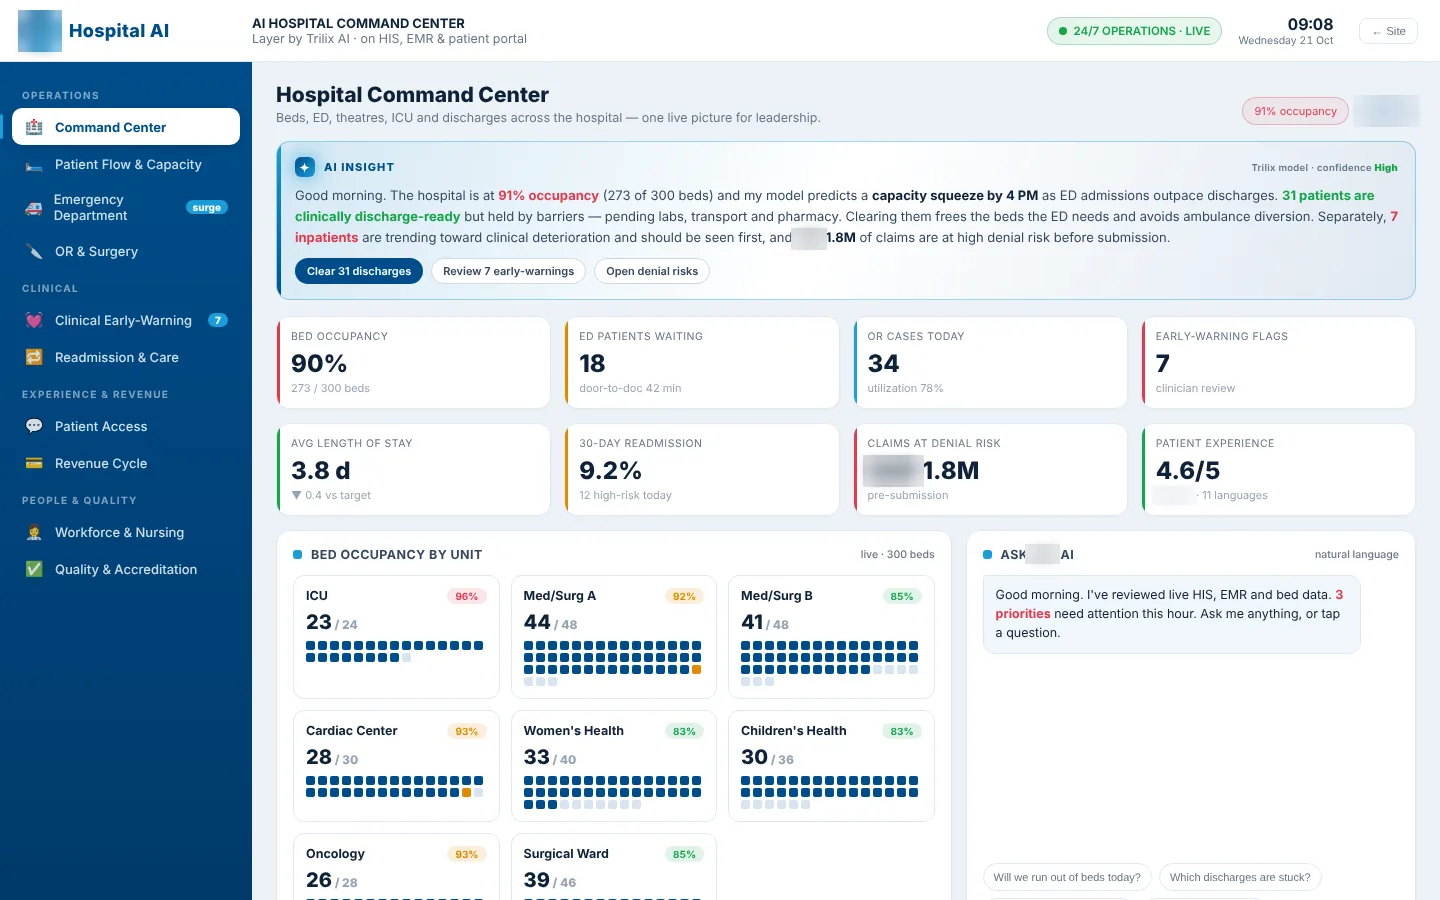
Occupancy unit by unit, emergency waits, theatre cases, early-warning flags, length of stay, readmissions, claims at risk and patient experience, with the priorities for the shift on top.
Beds, the emergency department, theatres, claims and staffing on one screen, with clinical decisions left to clinicians.
This is a demo build. It runs on sample data. We keep the hospital's name private.
At a glance
Demo build, sample data
Every hospital fights over the same scarce things: beds, theatres, emergency capacity and nurses.
A patient is ready to go home at 10 a.m. and is still in the bed at 4 p.m., waiting on a lab result, transport or discharge meds. Meanwhile the emergency department fills up. Theatres start late. A claim is denied for a missing pre-authorisation that could have been fixed before it went out. Accreditation evidence gets pulled together in a rush before each survey.
The data is in the hospital information system and the medical record. Nobody has it on one screen.
Occupancy unit by unit, emergency waits, theatre cases, early-warning flags, length of stay, readmissions, claims at risk and patient experience, with the priorities for the shift on top.
It predicts the evening census and lists discharge-ready patients held up by labs, transport, pharmacy or social care. Each blocker goes to the team that owns it.
Emergency surge forecasts, theatre scheduling, an early-warning watchlist, readmission risk, pre-submission claim checks, nurse staffing and accreditation evidence.
How the hospital actually runs. Its systems, how bed management and discharge work on the floor, and which problems leadership wants solved first.
Strict privacy controls. We connect the hospital and records data with access rules the hospital sets.
A first version in about 10 days, usually patient flow and the revenue cycle. The rest is switched on in order.
The hospital owns its data and the platform.
See also AI for clinics and healthcare and executive dashboards.
Book a call and we'll take you through the demo, from bed flow to claims.